Contact Info

 Qatar Clinics
How does a clinic ERP consultant help outpatient groups in Qatar?
For dental, dermatology, physiotherapy and family medicine groups in Qatar, a clinic ERP consultant designs the finance and stock layer behind the practice management system. I work out practitioner revenue share, insured and self-pay collections, prepaid treatment courses, consumables by branch and a profit view per location. Appointments and records stay in the clinic system, and I compare platforms independently and support delivery remotely.
Last reviewed by Vikas Saroj
Outpatient care in Qatar is often delivered by compact groups: a dental practice that opened a second branch, a dermatology and aesthetics center with a sister clinic, or a family medicine provider with locations in different parts of Doha. Owners know their patient volumes, yet few can say with confidence which branch or practitioner earns a profit after consumables and staff cost.
I help those owners build a back office that matches the size of the business. We begin with the money trail: how a day's takings become bank deposits, what each practitioner is owed, how insured visits turn into payer balances and where expensive consumables go. Booking, clinical notes, imaging and insurance submissions remain in the clinic management system, and the ERP only receives what finance and stock control need.
 What I Do
I design the finance, stock and payout side of a clinic group so it scales with each new branch, without touching clinical workflows.

Writing down each contract model in use, from fixed salary to percentage of collections, with deductions for lab work or materials, so payouts follow agreed rules and are not rebuilt in a spreadsheet each month.

Designing the daily close for every branch: card terminals, cash, transfers and refunds reconciled to a summary from the clinic system, with differences flagged for a named person instead of discovered at audit.

Setting up payer accounts and summary postings so insured visits show as balances by payer and branch, with settlements and rejected amounts recorded at a level finance can manage.

Stock design for dental materials, injectables, dressings and orthodontic supplies, including batch and expiry, plus external laboratory charges linked to the cases that caused them.

A repeatable template for a new branch: cost center, stock location, user roles, price list and reporting lines, so expansion does not break the reports owners already rely on.

Comparison of platforms and of the clinic system's own billing add-ons against your scenarios, with a written recommendation and support through testing, at no commission from any vendor.
What to Measure
An ERP for clinics should make these numbers available without a spreadsheet. I design the data model and reports around them from the start.
Platform Fit
How I Work
Follow the money in each branch
 Daily takings walk-through
Practitioner contract review
Consumables usage patterns
Clinic system exports
Rules, reports and a shortlist
Payout calculation rules
Branch and entity structure
Owner report mock-ups
Vendor scenario scripts
Guide the rollout branch by branch
Pilot branch first
Payout parallel run
Stock count and opening
Owner review after close
In a typical outpatient group in Qatar, revenue arrives through several doors at once. Insured patients pay a co-payment at the desk while the balance is claimed from the payer. Self-pay patients settle by card or cash, and aesthetic or dental patients often pay a deposit for a course of treatment. Some corporate clients are invoiced monthly for employee checkups.
Each of those doors needs its own handling in the ledger. Co-payments are cash today; the payer portion is a receivable that may be settled partly, later. Deposits are a liability until treatment is delivered. Corporate accounts need credit terms and statements. When all of this is posted as one revenue figure per month, the owners lose sight of what is collected, what is owed and what is still to be earned.
My first workshop with a clinic group is usually a walk through one day's takings at one branch, from the first appointment to the bank deposit. That surfaces the rules nobody wrote down: who can approve a discount, how refunds are handled, which card terminal belongs to which entity. Those rules become the requirements, and the ERP design follows from them rather than from a vendor's standard demo.
Clinic groups in Qatar recruit dentists, dermatologists and therapists on a variety of terms. Some receive a fixed salary, others a salary plus a percentage, and visiting consultants may be paid purely on their share of collections. Deductions for laboratory work, implants or expensive materials are common, and the basis can be the billed amount or the amount actually received.
When those rules live in one finance manager's spreadsheet, every payout becomes a negotiation. I document each agreement as a rule: the revenue base, the share, the deductions, the timing and how insurer rejections are reversed. The clinic system exports completed services by practitioner; the ERP or a small calculation layer applies the rules and produces a statement each practitioner can check.
Where practitioners are employees, the variable portion flows into payroll and the Wage Protection System file. Where they are independent contractors, it becomes a payable. I keep the two routes separate because they have different HR and accounting consequences, and I ask your advisors to confirm how each contract type should be treated. The result is a payout that management can explain line by line, which matters when a senior practitioner questions a figure.
Clinic consumables are small in volume but high in value per unit: composite and implant components in dentistry, fillers and toxins in aesthetics, brackets and aligner costs in orthodontics. Many carry expiry dates, and some need refrigerated storage, which in Qatar's climate means paying attention to how stock is delivered and held at each branch.
I design stock with a location per branch and, where useful, per treatment room cabinet. Items are received with batch and expiry, issued against procedures through simple consumption kits rather than line-by-line entry, and counted on a regular cycle. Kits matter: a dental crown or a laser session uses a predictable set of materials, and posting the kit keeps cost per procedure realistic without slowing the clinical team.
External laboratory work is a separate flow. Crowns, aligners and prosthetics are ordered per case, invoiced by the lab and often recharged or deducted from a practitioner's share. The requirement is to match each lab invoice to an order reference, without patient details in the ERP, and to show lab cost by practitioner and service. Your clinical leads decide which products need special storage; the ERP records where stock is and when it expires.
Growth in a clinic group usually means a new branch, and each opening tests the back office. Will the new location be a separate company with its own license, or a cost center of the existing entity? Will it share stock with a nearby branch? Does it need its own bank account and card terminals? I settle these questions in a branch template so each opening follows the same steps.
On tax, I am not aware of a general VAT in force in Qatar, so clinic invoices today mainly need to be clear and bilingual where your patients and payers expect Arabic. Check the current position with your tax advisor. I still keep tax fields and invoice layouts flexible, because rules in the region change and a rebuild later is expensive. Entity-level books also need to be clean for any corporate income tax that applies to your ownership structure.
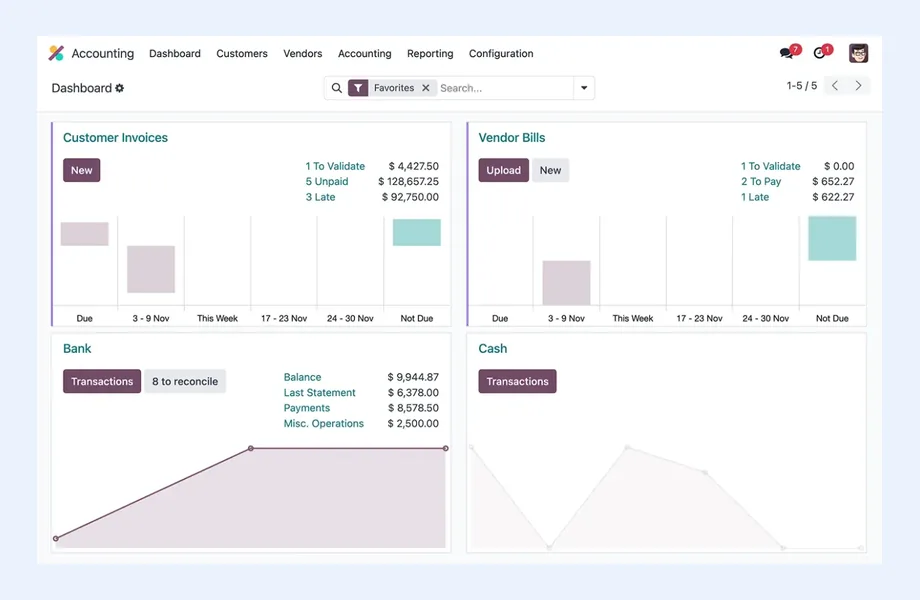
Reporting is where owners see the benefit. A branch profit view combines revenue by service, practitioner cost, consumables and rent, and a practitioner view shows activity against payout. I build mock-ups of those reports early, so the configuration serves the decisions owners actually make.
Most clinic groups already have a clinic management system they are comfortable with. The question is what sits behind it. For a single branch, the practice system's billing plus a small accounting package may be enough. Once there are several branches, practitioner agreements and serious consumables spend, a proper ERP usually earns its place.
Candidates such as Zoho, ERPNext, Odoo and, for larger groups, Microsoft Dynamics 365 get identical clinic scripts: a payer settlement with a rejection, a practitioner payout with lab deductions, a treatment course deposit and a stock count at a new branch. The interface with the clinic system is specified through system integration work, and payout rules come out of business process consulting.
Everything runs remotely, with short sessions scheduled around clinic hours so branch managers can join. For the general clinic model see ERP for clinics; hospital and multi-facility groups should read healthcare ERP in Qatar. Country-wide notes are on my Qatar ERP consultant page and the Qatar hub.

Tell me about your business and current systems. I’ll suggest the most sensible first step.
Book a Consultation
Not sure which ERP you need?
Share your business requirements with me and I will help you understand the right process, architecture and platform before implementation.
FAQ
Yes, as long as the rules are written down first. The clinic system provides completed services by practitioner, and the ERP or a small calculation layer applies the agreed share, deductions and rejection reversals. Employees are paid through payroll and contractors through payables. Your advisors confirm the treatment of each contract type.
Not always. If the clinic system handles billing well and stock is modest, good accounting software with clear procedures may be enough for now. I look at practitioner agreements, consumables spend and growth plans, and I will tell you if an ERP would add cost without a real benefit.
They stay in your clinic management system. The ERP receives service totals, practitioner activity and payer balances without patient identity or clinical notes. That keeps the ERP simpler and limits access to health information, and your compliance advisors confirm the data rules that apply.
A prepaid course is recorded as a liability when paid and recognized as sessions are delivered, using session counts exported from the clinic system. Refunds and expiries follow rules your finance team approves. The report shows how much of each course balance is still owed to patients at any point.
Every business is different. Share where you are today and what you want to fix, and I’ll tell you honestly whether and how I can help.
Book a Consultation
Insights
 Book a Consultation
Book a consultation to talk through your processes, systems and goals. I’ll reply with practical next steps - no obligation.