Contact Info

 Indian Healthcare
Why do Indian hospital chains need a healthcare ERP consultant?
For Indian hospital chains, diagnostic networks and multi-specialty groups, a healthcare ERP consultant designs the purchasing, pharmacy and central stores, asset, finance and HR processes that run beside the HIS. That includes batch and expiry control, TPA and scheme receivables, GST treatment of exempt and taxable income, consultant doctor payouts with TDS and cost per department. I map, specify, compare platforms independently and guide delivery remotely.
Last reviewed by Vikas Saroj
Indian hospital chains and diagnostic networks have expanded into new cities quickly, usually with a capable HIS handling registration, billing, pharmacy dispensing and lab orders. The back office has not always kept pace. Purchasing runs on email and phone approvals, each unit keeps its own store records, Tally holds the accounts, and TPA settlements are reconciled in spreadsheets.
I help promoters, CFOs and operations heads design an ERP that brings procurement, central and unit stores, pharmacy purchasing, biomedical assets, finance and payroll onto one platform. I start with the process: how an indent becomes a purchase order, how a batch moves from receipt to ward, how a TPA settlement reaches the bank and how consultant payouts are calculated.
Patient care, clinical records, OPD and IPD billing stay in the HIS, which your clinical and billing teams already know well.
 What I Do
I work on the business processes behind patient care and on the interface that keeps the HIS and the ERP in step.

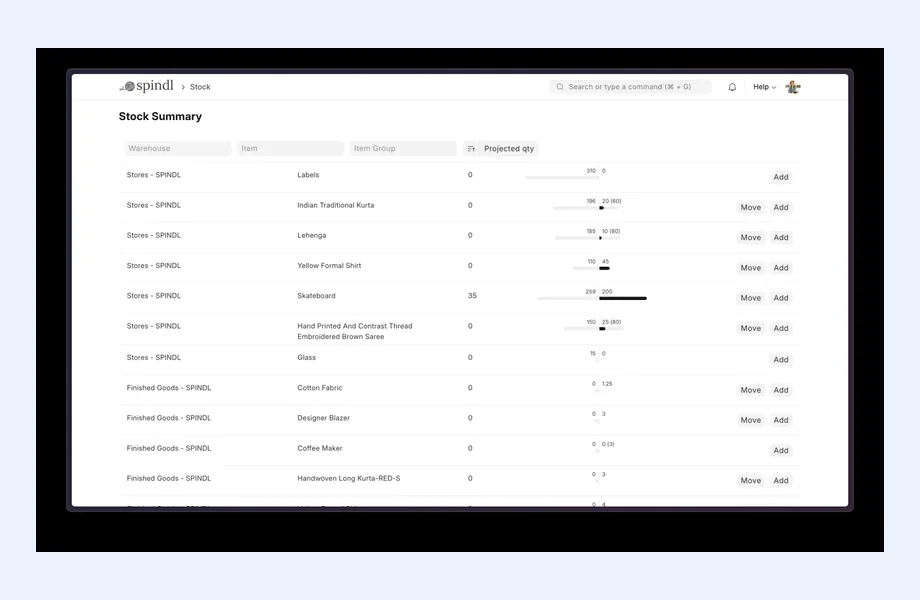
Tracing how wards, theater, labs and pharmacy raise indents, how approvals move by unit and value, and how rate contracts with distributors and manufacturers are applied at purchase order and invoice.

Central store, unit stores and in-house pharmacy with batch, expiry and MRP captured at receipt, inter-unit transfers, near-expiry alerts and returns to stockists, designed with your pharmacy and purchase heads.

A ledger, tax code and cost center design that reflects exempt healthcare services, taxable pharmacy and ancillary sales, input credit restrictions and TDS, confirmed with your chartered accountant.

Specifying how TPA, insurer and government scheme receivables, deductions and settlements reach the ERP from the HIS, and how consultant doctor shares are calculated, approved and paid with TDS.

Scripted demos built on one of your units and one month-end, scoring Zoho, Odoo, ERPNext and others on the same scenarios, with no commission from any vendor or implementer.

Guiding the implementer unit by unit: master data cleanup, stock opening by batch, user acceptance testing with store and pharmacy staff, and stabilization before the next unit goes live.
What to Measure
An ERP for healthcare should make these numbers available without a spreadsheet. I design the data model and reports around them from the start.
Platform Fit
How I Work
Walk the back office unit by unit
 Purchase and stores walkthroughs
Pharmacy batch handling review
TPA settlement reconciliation
HIS and Tally touchpoints
Requirements, GST scenarios and selection
Hospital BRD and priorities
GST cases with your CA
Unit-based demo scripts
Fit-gap scoring
Pilot unit, then the chain
Item master standardization
Batch-wise stock opening
Pilot unit go-live
Chain-wide rollout plan
Most Indian hospitals already run an HIS from a domestic vendor, covering registration, OPD and IPD billing, pharmacy sales, lab and radiology orders and discharge. Many of these products include basic stores and accounts screens, which works for a single hospital but strains when a group has several units, a central warehouse and a finance team that needs consolidated results.
The ERP's job is the business side: purchasing and rate contracts, central and unit stores, pharmacy procurement and valuation, biomedical assets, general ledger, payables, receivables from TPAs and payers, payroll costing and cost center reporting. The HIS remains the system for patient billing and dispensing, and sends the ERP summarized revenue by unit, department and payer, plus consumption and pharmacy sales movements.
Drawing that line early saves a great deal of rework. I document which system owns item, supplier, doctor, department and payer masters, and how codes are kept in sync. Identifiable patient data stays in the HIS; whatever must cross, such as an IP number for a consignment implant, is limited to the minimum and approved by your management and legal advisors. For a country-neutral overview, read my hospital and healthcare ERP page.
In-house pharmacies are a major revenue line and a major stock risk for Indian hospitals. Medicines are bought from distributors and stockists, received with batch number, expiry and MRP, issued to wards against indents or sold to outpatients at the counter, and returned to the supplier when they approach expiry under each supplier's return terms. Some drugs and devices are subject to price controls, so the selling price must come from a governed master rather than a pharmacist's memory.
The ERP design has to make each batch traceable from goods receipt to issue, show near-expiry stock early enough to return or transfer it, and value inventory consistently. I agree with your pharmacy and purchase heads which system records each movement: dispensing usually stays in the HIS, while purchasing, receipt, transfers, returns and valuation belong in the ERP, with an interface keeping quantities aligned.
Stents, orthopedic implants and other high-value devices are often supplied on consignment by distributors and billed only after use. When the OT records a used implant, that entry should generate the purchase order and store the lot or serial reference. Supplier drug license numbers and similar regulatory references belong on the supplier master. Compliance with drug and device regulations remains the responsibility of your pharmacy and regulatory team.
GST in healthcare is not straightforward. Healthcare services provided by clinical establishments are broadly exempt, while pharmacy sales to outpatients, some ancillary services and non-clinical charges can be taxable. Where income is exempt, the GST paid on related purchases generally cannot be claimed as input tax credit and becomes part of cost, and credits on common inputs may need apportionment. Some categories, such as certain room charges or cosmetic procedures, have had specific treatment. The rules change from time to time, so every scenario is confirmed with your chartered accountant.
For the ERP this means a clear set of tax codes on purchases and sales, a design for apportioning common credits, and purchase costing that includes non-creditable tax where required. Units in different states have separate GST registrations, so inter-unit transfers and shared services need deliberate treatment.
TDS is the other recurring requirement. Consultant doctors are often paid professional fees with tax deducted, contractors and rent attract their own sections, and certificates and returns depend on clean deductee masters. I write these as requirements and test them with your accounts team before go-live, alongside e-invoicing where it applies to your organization.
Cashless admissions under insurance are routed through TPAs and insurers, and many hospitals also treat patients under central or state government health schemes and corporate tie-ups. Settlements arrive with deductions and disallowances, often weeks after discharge, and some amounts are recovered later on appeal. Finance needs receivables by payer and scheme, with aging and a controlled process for write-offs. I design the summary that flows from the HIS and the matching of settlements to bank receipts.
Visiting and full-time consultants are frequently paid a share of the revenue they generate, calculated from HIS billing data under individual agreements. When this runs in spreadsheets, disputes and delays follow. The ERP or a controlled payout tool should take approved activity data, apply each doctor's terms, deduct TDS and post the cost to the right department.
With purchasing, consumption, payroll and payouts recorded by cost center, leadership can finally see cost per department, per bed and per unit. Accreditation audits also become easier when equipment maintenance and calibration records sit with the asset register rather than in separate files.
Most groups start from Tally for accounts, HIS stores modules and spreadsheets for assets and doctor payouts. Migration means standardizing item codes across units, opening stock by batch and expiry for each store, carrying over TPA receivables reconciled to the HIS, and loading supplier, asset and employee masters. A pilot unit followed by a phased rollout keeps risk manageable.
I evaluate Zoho, Odoo and ERPNext, which are common choices in India, alongside Microsoft Dynamics 365 for larger groups, and I will tell you if your HIS vendor's own modules cover enough. Work runs remotely in Indian working hours, with recorded sessions for store and pharmacy staff on shifts and training material in the language your teams prefer. Typical scope includes a BRD, gap analysis and implementation oversight.
Pharmacy distributors and manufacturers should see ERP for pharmaceuticals, and polyclinic chains ERP for clinics. India-wide subjects such as e-way bills and Tally migration are on my India ERP consultant page and the India hub.

Tell me about your business and current systems. I’ll suggest the most sensible first step.
Book a Consultation
Not sure which ERP you need?
Share your business requirements with me and I will help you understand the right process, architecture and platform before implementation.
FAQ
Usually the split works better. Dispensing and patient billing stay in the HIS, close to clinicians and counters, while purchasing, receipt, transfers, expiry returns and valuation move to the ERP. An interface keeps quantities aligned so the pharmacy and finance teams see the same stock.
I write every scenario into the requirements: exempt services, taxable pharmacy and ancillary sales, non-creditable input tax, apportionment of common credits and inter-state units. Your chartered accountant confirms the treatment, and I make sure the system applies it consistently and test it before go-live.
Yes, in most cases. Approved billing data from the HIS is combined with each consultant's agreed terms to calculate the share, TDS is deducted and the cost is posted by department. I define the rules with your finance and medical administration teams before any build starts.
It depends on the number of units, pharmacy volume, in-house technical capacity and budget. Zoho, Odoo and ERPNext are all used in India, and Dynamics 365 suits larger groups. I compare them on your own scenarios before you commit to any vendor.
Every business is different. Share where you are today and what you want to fix, and I’ll tell you honestly whether and how I can help.
Book a Consultation
Insights
 Book a Consultation
Book a consultation to talk through your processes, systems and goals. I’ll reply with practical next steps - no obligation.